NFPA 70-2026 brings important updates to Article 517 with an increased emphasis on reliability, resiliency and maintainability in healthcare electrical systems.

Learning objectives
- Identify key changes to NFPA 70-2026, Article 517 and understand how the revisions increase the emphasis on reliability, resiliency and maintainability in healthcare electrical systems.
- Explain the major changes affecting emergency electrical systems for healthcare, including the removal of Article 700 applicability and where to find these requirements in Article 517.
- Apply the revised Article 517 requirements to healthcare electrical design.
NFPA 70 insights
- NFPA 70-2026, Article 517 places greater emphasis on reliability, resiliency and maintainability, with healthcare-specific electrical requirements increasingly consolidated within Article 517 rather than relying on Article 700.
- New requirements for temporary power connections, N+1 redundancy and Class 2 lighting systems can significantly affect electrical system design, equipment selection, space requirements and project costs.
Healthcare electrical design has always existed at the intersection of safety and reliability. While NFPA 70: National Electrical Code (NEC) has historically focused on electrical safety, the 2026 edition of the NEC expands Article 517 in a manner that more clearly recognizes reliability as a fundamental design objective within healthcare occupancies.
The revised scope language found in Article 517.1, Scope, reinforces this shift. The article now explicitly identifies reliability as a core objective alongside electrical safety. This reflects what most healthcare electrical engineers already recognize: A hospital electrical failure can quickly become a patient safety issue even when no traditional electrical hazard exists.
Taken collectively, the revisions throughout Article 517 demonstrate that the code continues its evolution beyond traditional electrical safety requirements and increasingly emphasizes reliability, maintainability and operational continuity within healthcare facilities.

Article 517 stands on its own
The most significant structural change is found in 517.26, Application of Other Articles. Previous editions relied on references to Article 700 for several emergency system requirements. In the 2026 edition, Article 517 is intended to stand largely on its own with respect to healthcare emergency power systems. The code now clearly states that “The requirements of Article 700 shall not apply.”
Many provisions previously found in Article 700 have been added directly into Article 517 (see Table 1). While this may appear administrative at first glance, it carries significant implications. Designers can no longer rely on what they knew to be true for certain emergency system requirements traditionally associated with Article 700 because many of the prior provisions have been updated and modified specifically for healthcare occupancies, reflecting the unique reliability expectations associated with hospitals and other patient care environments.
Table 1: Article 700 compared to Article 517
| Requirement | Former 2023 Article 700 reference | New 2026 Article 517 reference | Notes |
| Multiwire branch circuits | 700.19 | 517.15 | Clarifies multiwire branch circuits are not permitted on the life-safety branch. |
| Ground-fault protection | 700.31 | 517.17 | Clarifies indication-only requirements between generators and transfer switches. |
| Emergency system signage | 700.7 | 517.28 | Service entrance and bonding hazard signage added into Article 517. |
| Sources of power | 700.3 | 517.30 | Requirements expanded to address multiple on-site power sources and maintainability. |
TABLE 1: This table identifies selected requirements that formerly resided in Article 700 and their corresponding locations within Article 517. These requirements remain in Article 700 for traditional emergency systems outside of healthcare occupancies. Courtesy: Certus Consulting Engineers
Increased alignment with NFPA 99
Another theme throughout Article 517 is the continued alignment with NFPA 99: Health Care Facilities Code. Notable examples include the addition of Section 517.4, Electrical Service, and revisions to Section 517.7, Patient Care Space Risk Categories.
The new language in 517.4 recognizes additional off-site, utility-provided services and configurations permitted to supplement the service to a healthcare facility based on reliability. This section now aligns more closely with NFPA 99 and specifically identifies acceptable sources such as power production source, fuel cell systems, energy storage systems and healthcare microgrids. This reflects the somewhat significant changes occurring throughout the healthcare industry.
Large hospital campuses are increasingly evaluating alternatives to traditional utility-plus-generator architectures to increase reliability. Concerns involving utility reliability, fuel supply constraints, operational continuity and sustainability goals have pushed many owners toward hybrid energy strategies. These permitted use of distributed energy resources (DERs) that can be used in conjunction with an electric utility to address these concerns.
The new language in Article 517.7 revolves around patient care space risk categories and specifically states that spaces shall be designed to meet the appropriate category as defined in NFPA 99. Rather than redefining these categories within the NEC, Article 517.7 directs the designer to the corresponding NFPA 99 provisions. These categories range from Category 1 through 4 and more clearly connect electrical system requirements directly to patient risk. This means that instead of relying primarily on occupancy classifications and room types, the design approach focuses on the risk to the patient if a system fails (see Figure 1).
- Category 1 spaces are where failure could result in major injury or death.
- Category 2 spaces are where failure could result in minor injury.
- Categories 3 and 4 spaces represent progressively lower clinical risk.
The practical benefit is improved consistency between NEC requirements, NFPA 99 risk assessments and owner operational expectations.
Spaces exempt from Article 517 requirements
The updated Article 517.10, Applicability, provides additional clarification regarding spaces that do not need to comply with Article 517 requirements. Historically, the code referenced “business offices, corridors, waiting rooms, and the like in clinics, medical, and dental offices, and outpatient facilities.”
However, room names and functional descriptions continue to evolve. The revised language now clarifies the intent and generally identifies “spaces not intended for direct patient care” as exempt from many Article 517 provisions. For engineers, this reinforces the importance of understanding how each space functions rather than relying solely on occupancy classifications or department names.
Formal recognition for reconditioned equipment
Updates to Article 517.3, Reconditioned Equipment, introduce provisions related to reconditioned patient care equipment. Formerly addressed in Article 517.6, the previous language simply stated that the requirements for reconditioned equipment in Article 110 do not apply to patient care related electrical equipment. This language is now located in article 517.3 but clarifies the intent by detailing exactly what is permitted.
Instead of saying the former requirements do not apply, it states that reconditioned patient care-related electrical equipment is permitted to be installed. The revised language clarifies the intent by specifically identifying permitted equipment. Examples include MRI systems, CT scanners, fluoroscopy equipment, diagnostic equipment and similar imaging technology.
This revision recognizes that medical equipment is regulated under federal requirements, NEMA/MITA 1-2015: Good Refurbishment Practices for Medical Electrical Equipment. This is notable because many healthcare owners routinely incorporate refurbished systems as part of cost control and sustainability initiatives.
The code also introduces a reserved section identifying future provisions for reconditioned equipment that are not permitted. While no specific prohibitions currently exist, engineers should monitor future code cycles because this area appears positioned for additional development. For now, any equipment that is part of electrical infrastructure serving the reconditioned patient care equipment is still governed by the reconditioned equipment requirements in Chapters 1 through 4 of the NEC (see Figure 2).
Multiwire branch circuit restrictions expand
Article 517.15, Multiwire Branch Circuits, introduces new requirements regarding multiwire branch circuits. Previous editions already prohibited multiwire branch circuits serving patient bed locations. The 2026 edition expands this concept by stating that branch circuits serving life safety lighting and life safety power circuits cannot be part of a multiwire branch circuit arrangement. While this requirement may appear new, its origins can be traced to provisions that previously applied to healthcare occupancies through the applicability of Article 700.
With Article 517.26 now stating that the requirements of Article 700 no longer apply, this requirement was added and clarified in Article 517.15, using terminology specific to the essential electrical system by referencing “life safety” circuits rather than the broader term “emergency” circuits.
From a reliability standpoint, the reasoning is straightforward. Multiwire branch circuits inherently introduce shared neutral dependencies and increase complexity during maintenance and troubleshooting. Although these systems remain acceptable in many occupancies, a healthcare facility must prioritize operational reliability and isolation over installation efficiency.
Ground-fault protection changes
Article 517.17, Ground-Fault Protection of Equipment,remains relatively unchanged in the 2026 edition, with the following key addition. The code now clarifies that ground-fault trip protection with automatic disconnection is not required between generators and transfer switches or on the load side of transfer switches. Instead, ground-fault indication is required (without disconnection) at any on-site power source. This is an area where experienced healthcare engineers will recognize language that previously existed in article 700, but as mentioned earlier, the requirements of article 700 are no longer applicable so this previous code language now exists in 517.17.
Many healthcare engineers have historically preferred indication-only approaches for the emergency power system because automatic tripping can introduce unintended outages that create risks greater than the fault itself. This revision formalizes an approach that many healthcare engineers have historically preferred because it minimizes the likelihood of a ground-fault event unnecessarily disconnecting emergency power loads.
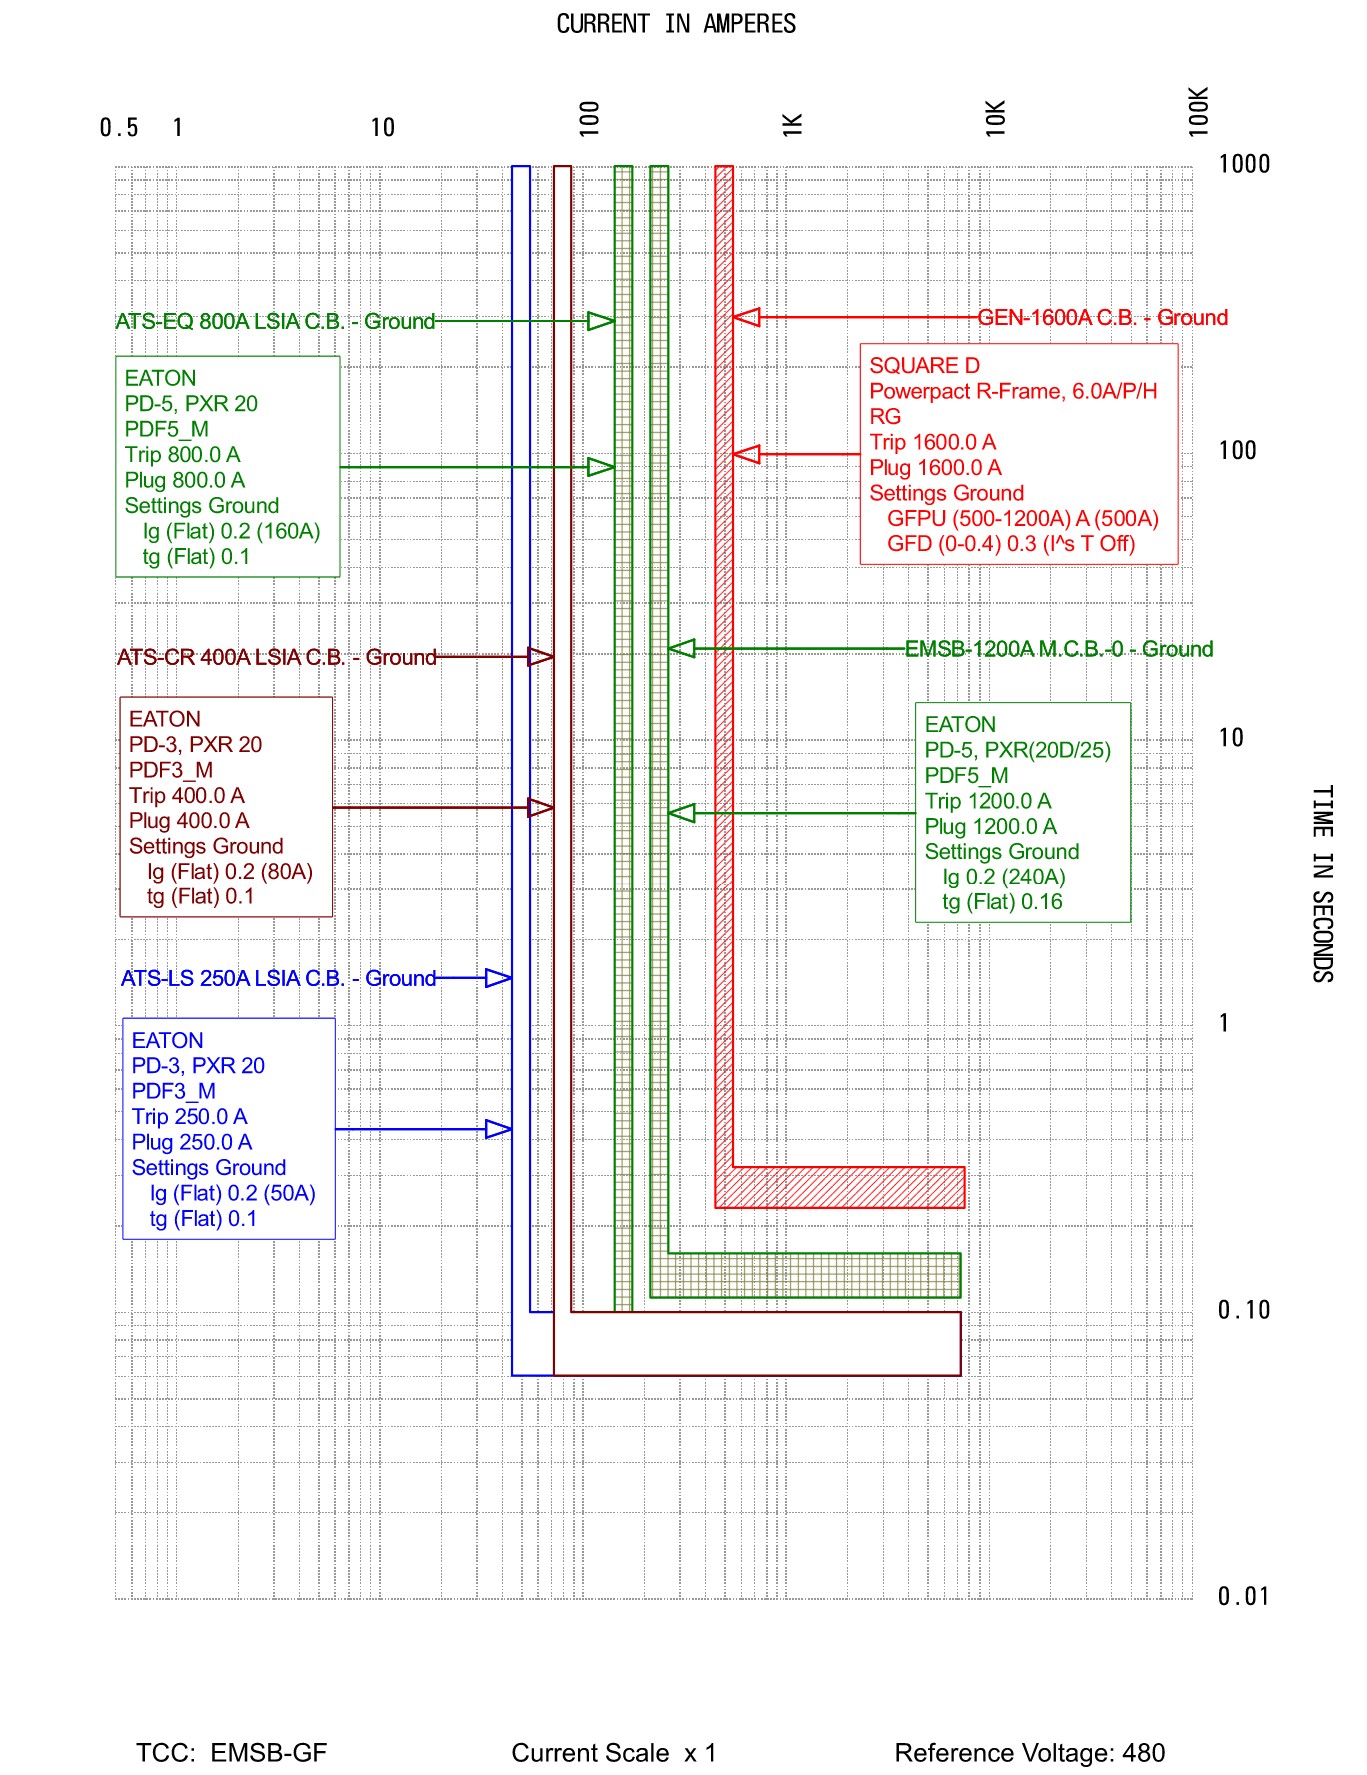
Further, while it remains unchanged in the 2026 edition, it is worth mentioning the selective coordination requirements of this article. Ground-fault protection requires complete selectivity throughout the entire available operating range (see Figure 3). While the code permits coordination for the trip regions outside of ground fault protection (long-time, short-time and instantaneous regions) to be limited through a duration of 0.1 seconds, Article 517.17 continues to require full selective coordination of ground-fault protection devices throughout the entire operating range. This distinction remains a key requirement in healthcare power system design.
New signage requirements
Article 517.28 introduces new signage requirements intended to improve operational awareness during emergencies and maintenance activities. This is yet another slightly modified section that previously existed in article 700 but is now added in 517. The new code section states “A sign shall be placed at the service-entrance equipment indicating type and location of each on-site power source.”
In modern facilities, this requirement becomes increasingly important as hospital electrical systems may include several power sources such as utility services, generator systems, battery energy storage systems, fuel cells and microgrids. Maintenance personnel and emergency responders must quickly understand how the facility is energized under abnormal operating conditions.
This section also echoes Article 700 with a requirement for a warning sign where removal of a bonding connection could create a hazardous condition while another source remains energized. The sign must include the exact language written in the code, “Warning: Shock hazard exists if grounding electrode conductor or bonding jumper connection in this equipment is removed while another source is energized” (see Figure 4).

Emergency systems that have a solid, unswitched neutral in the transfer equipment (non-separately derived) rely on the normal source grounding and bonding system as part of the ground-fault current return path. If a main or system bonding jumper is removed while another source remains energized, maintenance personnel could unknowingly become part of the fault-current path. The warning sign helps communicate this hazard before maintenance activities begin.
Temporary power connections
Perhaps the most impactful emergency power change in the 2026 edition appears in Article 517.30. Design professionals are likely familiar with requirements for temporary generator connections when only a single on-site generator is installed, which was first introduced in the 2017 version of the code. As with the last two discussion points, this requirement previously existed in article 700 but now also resides in 517.
However, what has changed is the treatment of facilities with multiple power sources. Historically, many engineers viewed parallel generator plants as inherently compliant because redundancy existed within the generator system itself. The 2026 code takes a different approach. Unless the emergency electrical supply system is truly designed with redundancy (N+1 capacity), facilities using multiple generators must now provide a means to connect a portable temporary power source when any single on-site source is removed from service (see Figure 5).
The requirements are extensive. Any emergency electrical system (EES) using more than one power source shall comply with all of the following points when any single on-site power source is disabled for service. As stated in 517.30(F):
- The EES shall include means for the connection of a portable or temporary on-site power source without modification to permanent system wiring or equipment. The temporary connection shall be sized to accommodate the largest power source.
- A documented sequence of operation for this connection and method for the connection of a portable or temporary on-site power source shall be permanently located at the connection point. The connection shall be sized to support the capacity of the load intended to be served.
- Integration of temporary power sources shall not impede the operation of the remaining operational on-site power sources or the timing of transfer switch operation as specified in 517.32. Mechanical or electrical interlocking shall prevent inadvertent interconnection of power sources.
- The connection point for the portable or temporary on-site power source shall be marked with the phase rotation and system bonding requirements and instructions for integration of start signal and annunciation wiring.
The practical challenge associated with this requirement is often underestimated. Most temporary rental generators are designed to operate as standalone units and may not possess the controls necessary to seamlessly integrate into an existing paralleling generator plant. As a result, compliance may require significantly more than merely providing a cam-lock connection cabinet. Designers should carefully evaluate synchronization requirements, control system integration, load pickup sequencing, bonding methods and operational procedures during early design phases.
The only exception is if the emergency power system is truly designed with redundancy such that the system has capacity to support the demand load of the life safety, critical and equipment branch with the largest power source disabled. This represents a significant shift in resiliency expectations. The code effectively recognizes that redundancy alone does not necessarily provide maintainability. A facility may still lose required capacity when a generator is removed from service for major maintenance or replacement.
Design teams should carefully evaluate future projects because compliance could influence generator paralleling switchgear, outdoor connection cabinets, control architectures and physical site planning. For many facilities, the simplest path to compliance may be demonstrating true N+1 capability, which has significant space and cost implications.
Life-safety lighting flexibility
Article 517.33 introduces language addressing means-of-egress illumination. Hospital corridors frequently operate with day and night lighting modes. The new language clarifies that switching arrangements are permitted when transferring corridor lighting between normal illumination and night illumination circuits, provided only that both systems cannot be extinguished simultaneously.
This seemingly minor revision addresses a practical operational issue that many hospitals encounter. Facility staff often desire reduced nighttime light levels for patient comfort while simultaneously maintaining life-safety expectations. The new language provides additional clarity regarding acceptable switching arrangements that support both objectives and mirror NFPA 101: Life Safety Code.
Spotlight on Class 2 lighting systems
Another forward-looking revision applicable to modern facilities can be found in Article 517.80. The new language states that Class 2 lighting circuit cabling supplied from critical or life-safety branch power must comply with Article 517 mechanical protection requirements. This change reflects a significant technological trend. Modern health care facilities increasingly employ low-voltage LED lighting with distributed lighting control systems using Class 2 wiring.
Historically, many of these systems have existed somewhat outside traditional emergency branch design discussions because they operate at limited energy levels. The code now clearly recognizes a potential reliability concern associated with the rapid adoption of low-voltage lighting systems. While the energy available from these systems may be limited, loss of lighting function itself can still have significant operational consequences in patient care spaces served by the life-safety or critical branches of the essential electrical system.
The enhanced explanatory material further reinforces a foundational principle of Article 517, “minimizing patient exposure to potential electrical hazards while maintaining reliable operation of essential systems.” Designers should expect greater scrutiny regarding mechanical protection methods and routing of Class 2 circuits. As healthcare facilities continue to adopt digital lighting platforms, this provision will likely become increasingly important.
Looking ahead
While many of the modifications contained in the 2026 edition of Article 517 appear relatively small when viewed individually, a much larger trend becomes apparent when they are considered collectively. The code continues its evolution beyond traditional electrical safety requirements and increasingly emphasizes reliability, resiliency and maintainability within health care electrical systems.
Expanded recognition of DERs, incorporation of patient-risk-based design concepts from NFPA 99, new expectations regarding temporary power connections and protection of emerging Class 2 lighting systems all reflect an industry adapting to new technologies while maintaining commitment to patient safety.
Perhaps most importantly, Article 517.26 establishes a clearer separation between healthcare electrical systems and the general emergency system requirements found elsewhere in the NEC. Rather than relying on generalized emergency power provisions, the code increasingly provides healthcare-specific requirements tailored to the unique operational expectations of hospitals and patient care facilities.
For consulting engineers, these revisions serve as a reminder that code compliance alone is never the primary objective. The goal remains designing electrical systems that continue to operate when patients depend on them most.